
Frailty Pathway
Who is this for?
•Target population: This pathway addresses the complex needs of older adults (generally 65 and older) living with or at risk of frailty through early identification, proactive intervention, and multidisciplinary collaboration.
•Pathway entry considerations: One or more may prompt entry into the pathway:
-Age (cut-off determined by clinic and/or organization)
-Geriatric Syndrome(s)
-Multi-morbidity
-Psycho-social Concern(s)
Pathway Information
Select the most appropriate decision tree based on where the patient resides.
Download the pathways:
Kawartha Lakes
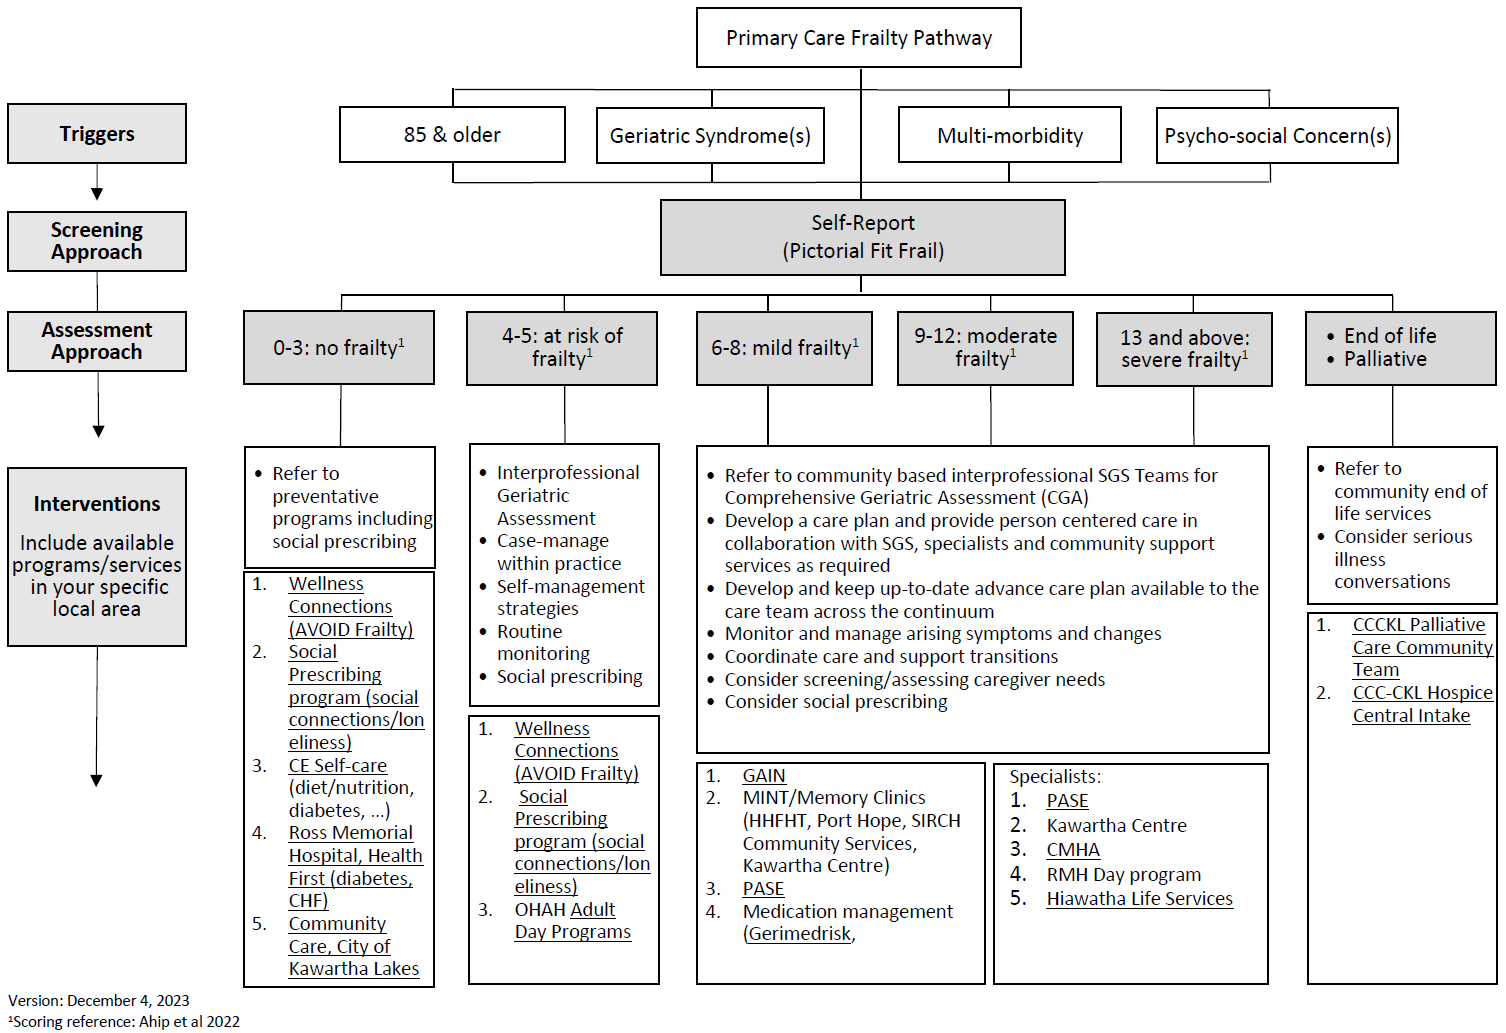
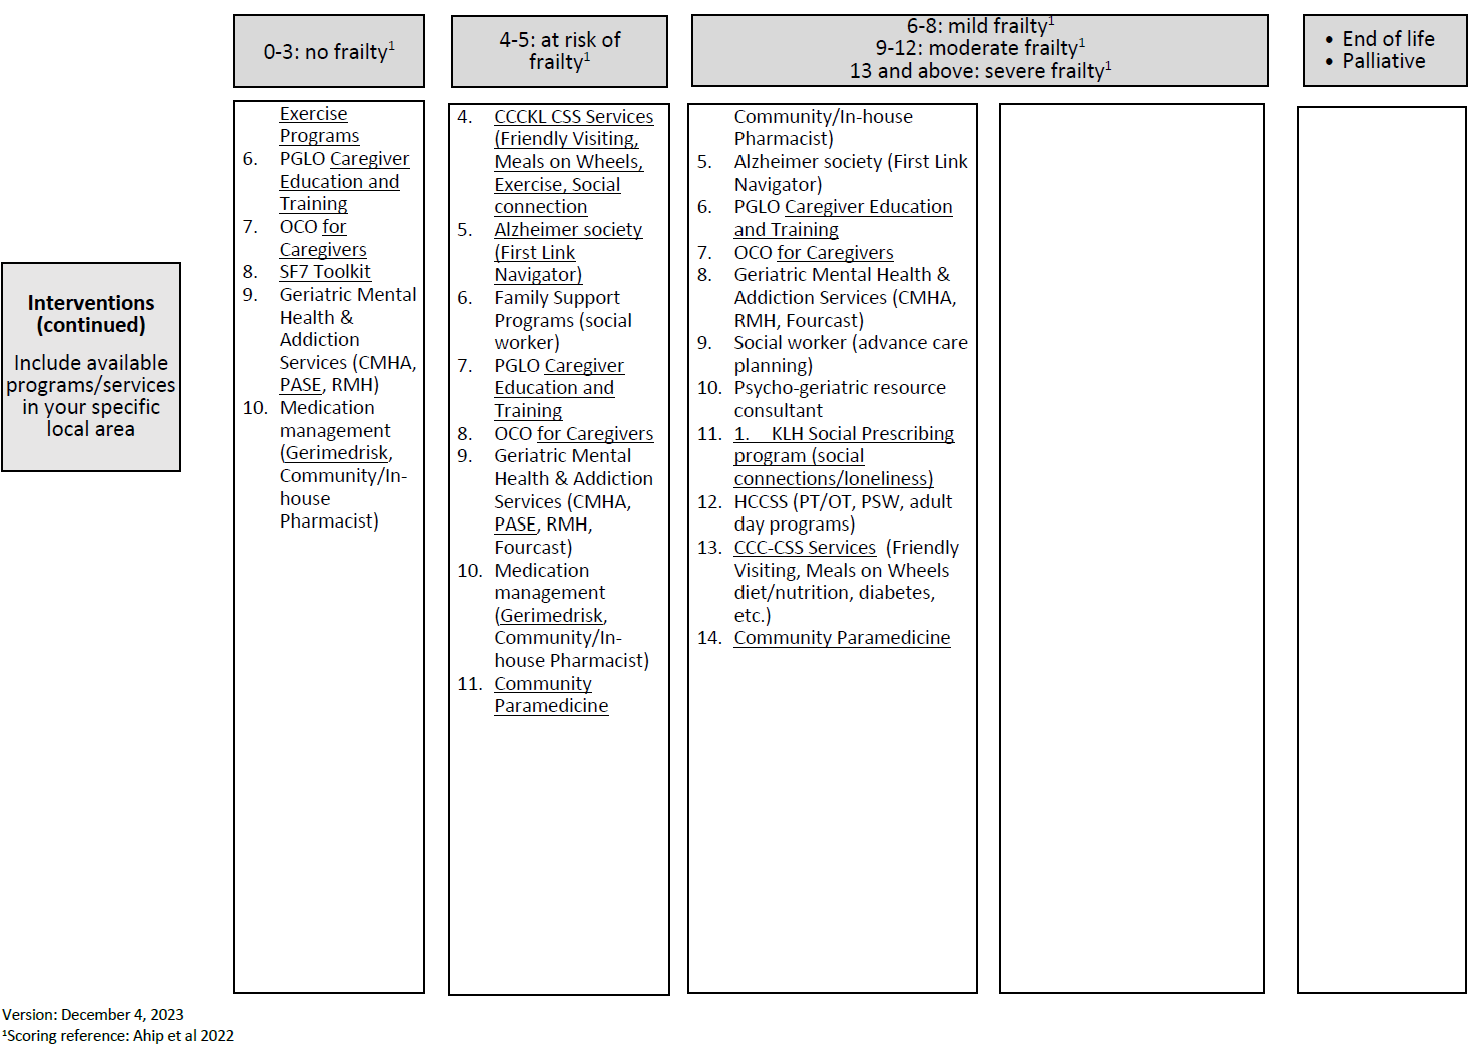
Haliburton County
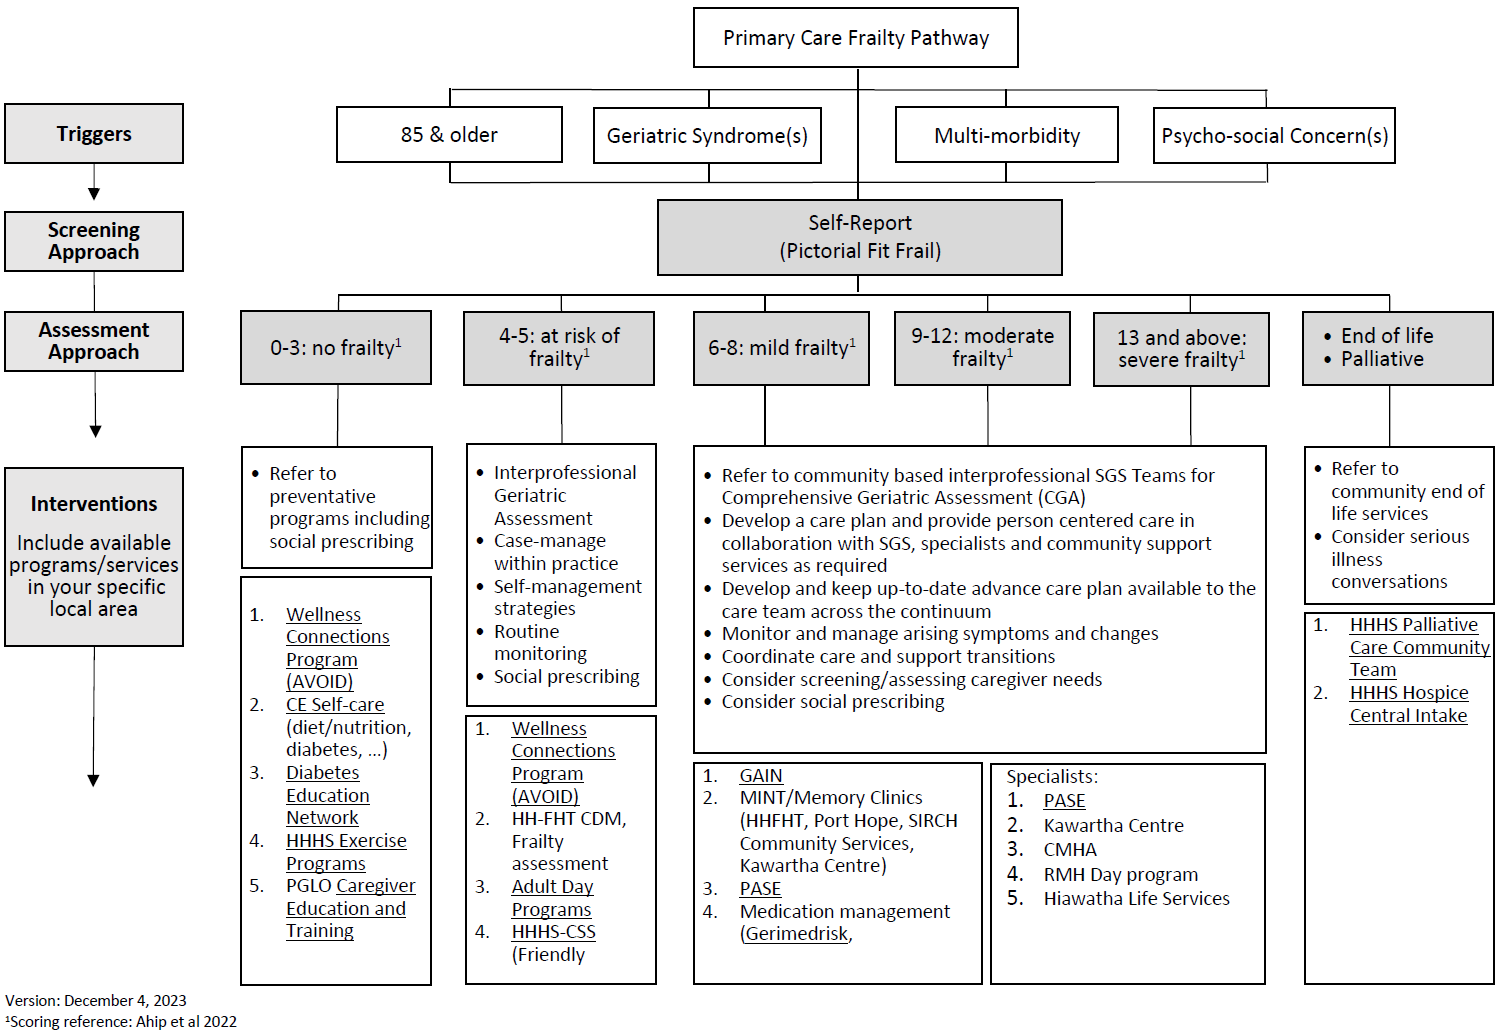
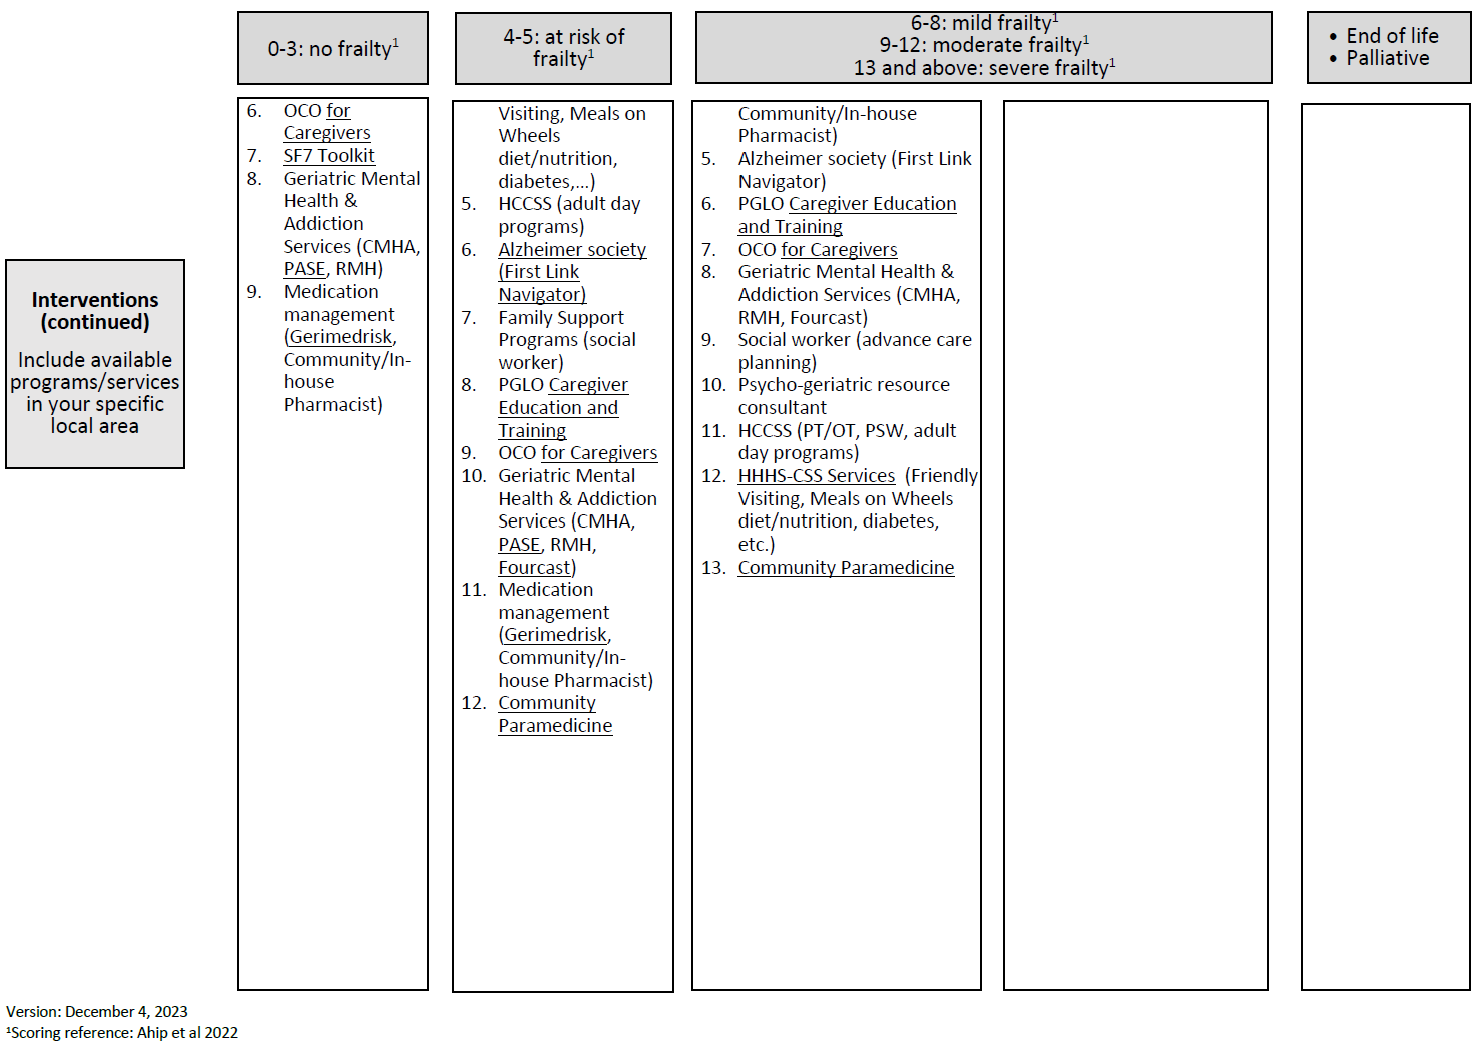
Additional Information
Patient/Client Facing Resources
Patients or clinicians can refer to the Wellness Connections Program after a frailty screen has been completed: https://search.caredove.com/org/service/30182
Clinical Context
Older adults constitute 28% of the total population in Kawartha Lakes, and 32% of the total population in Haliburton County, both significantly higher than the Provincial average of approximately 18%. Many of these individuals are living with multiple, chronic and complex health & social conditions including frailty and dementia.
According to the Canadian Frailty Network, frailty is a state of increased vulnerability, with reduced physical reserve and loss of function across multiple body systems. Frailty is a predictor of death, heightened vulnerability, institutionalization and a reduced quality of life.
As proposed by the Ontario Collaborative of Aging Well [Consensus Statement: Care for the Older Adult with Complex Health Conditions - Reframing ‘Frailty’ in an Ontario Context - Provincial Geriatrics Leadership Ontario], the concept of frailty must include the physical, cognitive, mental, and social health of older adults and their care partners, and the interaction and integration of these four domains.
Unmanaged frailty is among the drivers of Alternate Level of Care (ALC) rates in the province. According to the Provincial Geriatrics Leadership Ontario(More than 1.1 million Ontario older adults may be living with frailty by 2040 - Provincial Geriatrics Leadership Ontario), by 2030, individuals living with frailty are estimated to rise by at least 20%; this is important as we recognize that even in the current state, we at KLH-OHT, do not have the ideal pool of community resources to best meet the needs of this clientele.

Best Practice
Evidence(ALC Leading Practices: Supporting Ontario Health Teams to Influence Alternate Level of Care - Provincial Geriatrics Leadership Ontario) suggests that implementation of proactive frailty screening & identification, and promotion of self-management strategies to prevent or stabilize frailty, directly contribute towards reducing unexpected hospitalizations, ALC designation, and the expression of LTC need.
Frailty screening can be leveraged to facilitate timely and coordinated access to a suite of preventative and specialized programs; as an upstream ALC avoidance strategy. All system partners including primary care can play a pivotal role in frailty management.
Developed by Seniors Care Network(Seniors Care Network | Geriatric), the Primary Care Frailty Pathways https://www.seniorscarenetwork.ca/frailty outline standardized approaches to prevention, identification, assessment, and management to support older adults with living in the community, and/or maintaining their function and independence.
Health Quality Ontario:
- Frailty in Adults: Care in All Settings (Quality Standard Details | Ontario Health) (IN DEVELOPMENT)
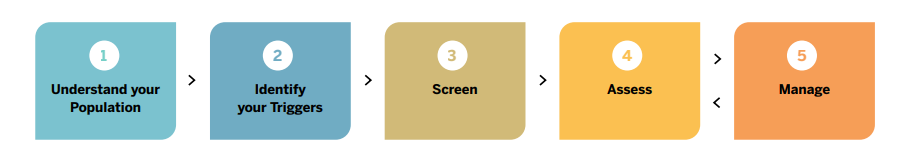
Source: PGLO 2023
Need Help and Feedback
If you need assistance with any part of this pathway, including understanding the process, accessing forms, digital implementation, or reporting technical issues, please contact us. We welcome your feedback and suggestions for improvement.
info@klhpcn.ca
Please expect a response in 1-2 business days.
Total
28.5 hours over a minimum of 6 weeks


